Phalloplasty
What does phalloplasty involve? How do you prepare for the surgery and what can you expect afterwards? Below you can read about the procedure, the risks involved and the post-operative period.
About phalloplasty
Phalloplasty is a surgical procedure in which a penis (phallus) is created using tissue taken from elsewhere in the body, such as the arm, flank or leg. The technique used depends on your physical characteristics and preferences. Phalloplasty can result in a penis of average to above average size. Because the penis is made from skin tissue taken from elsewhere, there is limited sensation in the penis when touched. Sensation may improve over time, but usually remains very little. Permanent scars will form at the site(s) where the tissue was removed, these scars can be large in size.
Without urethral lengthening
With phalloplasty, the penis can be created with or without urethral lengthening.
Following a phalloplasty without urethral lengthening, you will urinate whilst sitting, from behind the scrotum. Without urethral lengthening, your vagina can be preserved. A phalloplasty without urethral lengthening carries an approximate 5% risk (1 in 20 people) of medical problems (complications).
With urethral extension
Following a phalloplasty with a urethral extension, the urethra ends somewhere in the shaft of the penis or at the tip of the penis. How far the urethra extends depends on the technique used to create it. Where the urethra ends will affect your ability to urinate whilst standing. If the urethra only extends halfway down the penis or even shorter, it will be very difficult, or sometimes impossible, to urinate whilst standing. For a phalloplasty with a urethral extension, the vagina and uterus must be removed prior to the operation. A disadvantage of urethral lengthening is that the procedure carries a very high risk of complications. Complications occur in over 80% (more than 8 out of 10 people), and usually one or more extra operations are needed to resolve the problems. Sometimes permanent problems with urinary function arise. Furthermore, urethral lengthening does not guarantee the ability to urinate whilst standing; approximately 70 per cent (7 out of 10 people) are able to urinate from the tip of the penis whilst standing after urethral lengthening. Often, several operations are required before this becomes possible. These complications are in addition to the risks and recovery time associated with the preparatory colpectomy operation.
To be eligible for a phalloplasty, you must be fully informed and meet several criteria. You can find more information about preparing for genital surgery here. Further details about phalloplasty can be found in
the animated videos produced by Amsterdam UMC..
The operation
The phalloplasty is performed by a one or two plastic surgeons in collaboration with a urologist. The penis and the urethral extension can be created using various techniques. The duration of the operation can vary between around 3 hours to over 6 hours. This length of the operation depends on the complexity of the technique used with more complex techniques requiring more time.
The details of the operation may vary from one healthcare facility to another. It is therefore important to check the exact procedure that you will have with the healthcare facility where you are having the operation.
Start of the operation
The urologist will insert a urinary catheter, which is a small drainage tube inserted via the urethra. If you are having a urethral lengthening procedure, you will also be fitted with a bladder catheter, which is inserted through the abdomen.
Creating the scrotum
The scrotum is created in a similar way for phalloplasty with and without urethral lengthening. The clitoris and the inner and outer labia are dissected. Then, in a phalloplasty with urethral lengthening, the urethra is lengthened slightly using the inner labia. In a phalloplasty without urethral lengthening, this step is omitted; instead, the urethra will emerge from behind the scrotum.
Next, the outer labia and the skin of the pubic area are brought together and sutured over the catheter to form the first extended section of the urethra. The scrotum is now formed, and the genital area is ready for attachment of the penis.

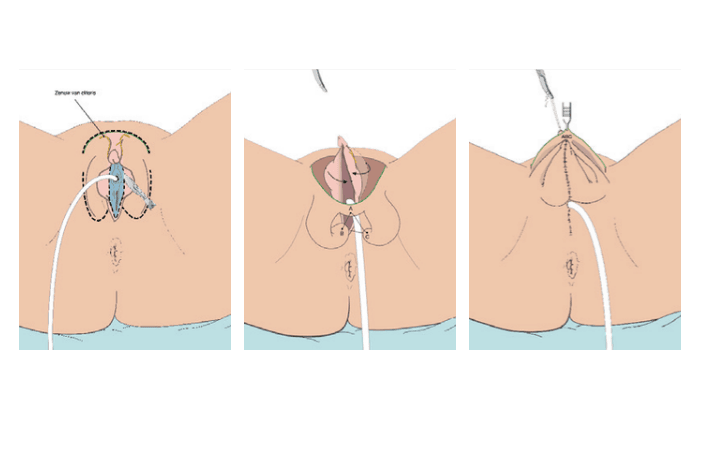
In phalloplasty without a urethra, the penis (phallus) is constructed in a similar manner, with the only difference being where the donor skin is taken from. Phalloplasty without a urethra is performed by a urologist and a plastic surgeon.
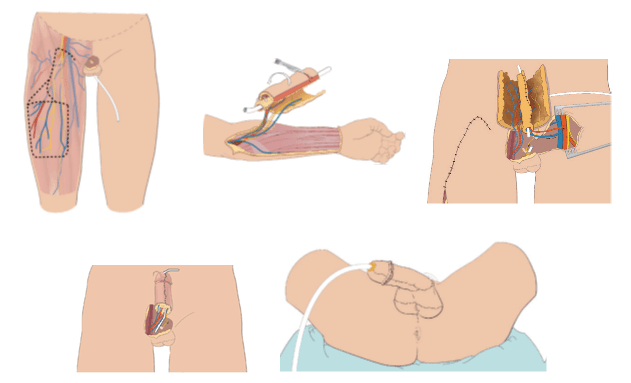
In all techniques, the urologist creates the scrotum as described above. Meanwhile, the plastic surgeon works on the donor skin. A skin flap measuring approximately 13 cm by 13 cm is marked out; this will serve as the donor skin for the penis. The marked out area of donor skin should contain a vein, an artery and two nerves. This ensures that the donor skin retains its blood supply and sensitivity. The flap of donor skin is detached, and with the aid of a microscope, the blood vessels of the donor skin are connected to the blood vessels in the lower abdomen. The nerve is connected to one of the two nerves of the clitoris. This allows sensation to be established in the penis. The skin is shaped into a penis and sutured in place. The wound where the donor skin was taken from can be closed in various ways, usually with a thin strip of skin from the thigh.
The following surgical techniques can be used for phalloplasty without a urethra:
- Phalloplasty without a urethra – donor skin from the forearm (FRFF)
- Phalloplasty without a urethra – donor skin from the flank (SCIP)
- Phalloplasty without a urethra – donor skin from the thigh (ALT)
Below you can read more about the specific details of the various techniques.
1. Phalloplasty without a urethra – donor skin from the forearm (FRFF)
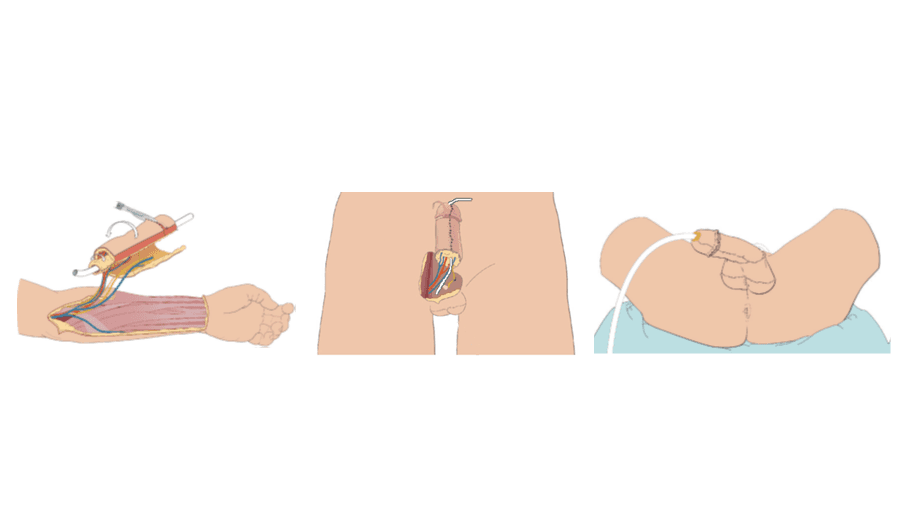
In this technique, skin from the forearm is used to create the shaft of the penis. An area of skin measuring approximately 13 by 13 cm is marked out on the forearm (see figure). This becomes the donor skin for the penis. The exact dimensions depend on the length of the forearm. The wound on the forearm is closed using skin taken from the thigh.
Scars
This technique results in a large, noticeable scar on the arm where the skin was removed and a less noticeable scar on the thigh (resembling a graze).


2. Phalloplasty without a urethra – donor skin from the flank (SCIP)
In this technique, skin from the flank (the side) is used to form the shaft of the penis. An area of skin measuring approximately 13 by 13 cm is marked out on the flank. This becomes the donor skin for the penis. The wound on the flank is sutured closed; this usually does not require any additional skin.
Scars
This technique results in a large scar on the flank where the skin has been removed. This will largely fall within the natural creases of the flank, making it a less conspicuous scar.
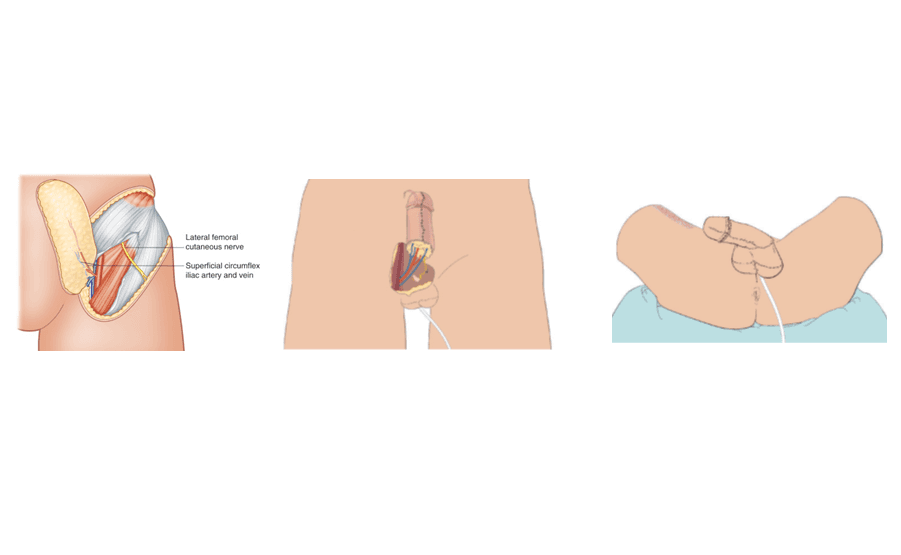
3. Phalloplasty without a urethra – donor skin from the thigh (ALT)
Please note: this technique is rarely used nowadays; it is no longer common practice to use donor skin from the thigh.
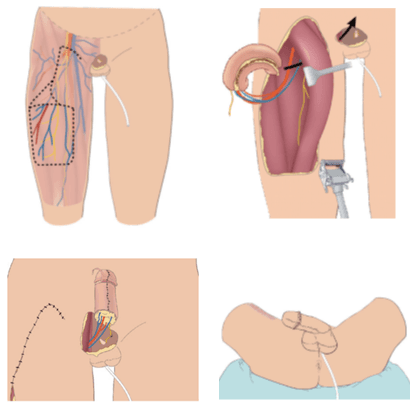
In this technique, skin from the thigh is used to form the shaft of the penis. An area of skin measuring approximately 13 by 13 cm is marked out on the thigh; this becomes the donor skin for the penis. The skin is rolled up and sutured into the shape of a penis. The penis is then moved subcutaneously, beneath the leg muscles, to the genital area. The wound on the leg is closed, often using skin taken from the other thigh.
Scars
This technique results in a large scar on the thigh where the skin has been removed, sometimes accompanied by a dent. If extra skin is needed to close the wound, this will also result in a large shallow scar on the other leg.

Creating the penis (phallus) with a urethra
In all techniques for a phalloplasty with a urethra, the penis (phallus) is constructed in a similar way; only the source of the donor skin for the urethra and the penis differs. A phalloplasty with a urethra is performed by a urologist and a plastic surgeon (sometimes two).
In all techniques, the urologist first creates the scrotum as described earlier. Meanwhile, one plastic surgeon works on the donor skin for the urethra. The plastic surgeon(s) is working on the donor skin for the penis. For the urethra, a piece of skin measuring approximately 3 by 17 cm is marked out and excised. This skin is rolled around the urinary catheter and sutured in place to form a urethra. The donor skin for the penis measures approximately 13 by 13 cm and contains a major blood vessel, an artery and nerves. This ensures that the donor skin remains well-perfused (receiving a regular blood flow) and sensitive. Using a microscope, the blood vessels of the donor skin are connected to the blood vessels in the lower abdomen. The nerves are connected to one of the two nerves of the clitoris, allowing sensation to be transmitted to the penis. The donor skin is shaped into a penis and sutured in place. The wound from the donor skin used for the urethra is closed with sutures. The wound from the donor skin used for the penis can be closed in various ways.
You can read more about the details of the various techniques below.
The following surgical techniques can be used for phalloplasty with a urethra:
- Phalloplasty with urethra – donor skin from the forearm (urethra and shaft)
- Phalloplasty with urethra – donor skin from (among other areas) the flank (shaft) and vulvar lip tissue (urethra)
- Phalloplasty with urethra – donor skin from the thigh or flank (shaft) and from the forearm (urethra)
1. Phalloplasty with urethra – donor skin from the forearm
In this operation, both the urethra and the shaft of the penis are constructed from skin taken from the forearm. Phalloplasty using a urethra from the forearm is the technique most used worldwide. The donor site for the urethra is sutured, and the donor site for the penis is closed using skin taken from the thigh.
Scars
This technique results in a large, noticeable scar on the arm where the skin was removed and a less noticeable scar on the thigh (resembling a graze).
2. Phalloplasty with urethra – donor skin from (among other areas) the flank (shaft)
In this phalloplasty procedure, the shaft of the penis is created using skin from the flank. The urethra can be constructed in various ways: using skin from the forearm, tissue from the labia minora, or skin from the other flank (this depends on your preferences and physical characteristics). The incision on the flank is closed with sutures; this usually does not require any additional skin.
Scars
This technique results in a large scar on the flank where the skin has been removed. However, this will fall within the natural crease of the flank, making it a less conspicuous scar. You may also have a smaller scar elsewhere, where the skin was removed to create the urethra.
3. Phalloplasty with urethra – donor skin from the thigh or flank (shaft) and from the forearm (urethra)
Please note: this technique is rarely used nowadays; it is no longer common practice to use donor skin from the thigh.
In this phalloplasty, the urethra is created using skin from the forearm and the shaft is created using skin from the thigh or flank. The wound on the forearm is sutured closed. The wound on the leg is closed using skin taken from the other thigh. If the shaft is created using skin from the flank, this wound can usually be sutured closed, and no skin graft is required.
Scars
This technique results in a large scar on the thigh or flank, where the skin has been removed. This will fade increasingly over time as it is a superficial wound. You will also have a smaller scar on the other arm, where the skin has been removed.
Aftercare
It is advised that you only move gently immediately after the operation. If you are sufficiently independent, including being able to look after your wounds and are able to pass stool, you may in principle, go home. The doctor will let you know when you are ready to go home, this is usually after 2–3 days. If you have a wound on your forearm, the dressing will be removed after 5 days. A wound on the leg will remain dressed for as long as possible. Should it start to ooze, the wound will be undressed and re-dressed.
Aftercare depends on the healthcare facility. Regardless of the technique used, you will have regular check-ups with the plastic surgeon and the urologist after the operation. The plastic surgeon will check the appearance and the wounds on the penis. The urologist will check the urethra and urinary function using urinary tests and questionnaires. If complications arise, you will need to visit the hospital more frequently. You must care for the catheter(s) and wounds as explained by the nurse at your healthcare facility.
It is advised to wait until the wounds have completely healed before you go swimming, have a bath or visit the sauna. This takes at least six weeks. This is to prevent the stitches from dissolving too early and to avoid infections in the wound. However, you are allowed to take a short shower. You should not exercise or lift heavy objects for six weeks, as this can cause bleeding or excessive fluid build-up. Additionally, you must wear tight-fitting underpants or mesh briefs for six weeks to ensure the penis hangs straight down.
It is strongly advised not to smoke for at least three months after the operation.
Further information on aftercare, results and complications can be found in this animated video from Amsterdam UMC.
Complications and risks during and after the operation
Unintended medical problems (complications) may arise during or after treatment, even if the operation has been carried out correctly. The risk of complications depends on the technique used. Techniques involving the creation of a new urethra carry a high risk of complications. A phalloplasty with urethral lengthening carries up to a 70% risk of complications while a phalloplasty without urethral lengthening carries approximately 5% per cent risk of complications.
- (Post-operative) bleeding: This usually occurs immediately after the operation. Depending on the severity, a second operation may sometimes be necessary to stop the bleeding.
- Wounds opening up again. Wounds may open, for example, because sutures come apart prematurely. You must take good care of your wounds, as re-suturing is not possible.
- Wound reopening: Wounds may reopen, for example because the stitches come loose prematurely. You must look after the wound properly, as it is not possible to re-stitch it.
- Impaired wound healing: Wounds can develop, particularly around the stitches. This has a higher risk in people who smoke, but sometimes can also happen in non-smokers. This generally heals by itself, but it can take a long time. Rinse the wounds regularly with lukewarm tap water and pat the affected area dry. Problems with wound healing are common.
- Necrosis (dying tissue): If the skin is not properly supplied with blood, it dies. Smokers are at increased risk of this. Sometimes this is already apparent during an operation and blood flow is improved straight away. Sometimes it occurs after the operation. It usually heals on its own, but occasionally a corrective operation is needed.
- Infection: Although the procedure is carried out under sterile conditions, there is always a risk that bacteria may enter the surgical wound. This can also happen at home. That is why it is important that you look after the wounds properly. If the skin around the wound becomes warm and red, if there is discharge from the wound, or if you develop a fever, this may indicate a wound infection, and you should contact your doctor.
- Urination problems (urethral stricture): The urethra may become narrowed (stricture), making it difficult to pass urine. Urethral strictures are treated by a urologist. Sometimes this requires further surgery. Without urethral lengthening, the risk of a stricture is 5%; with urethral lengthening, it rises to 70%.
- Urination problems (fistula): During the healing process, the extended urethra may form an abnormal connection with the skin, causing urine to leak from this opening when you urinate. This is called a fistula. Sometimes this heals on its own. If this does not heal on its own you may need surgery. Urethral lengthening carries a higher risk of a fistula (50%) than without urethral lengthening (5%)
- Urination problems (dribbling): Dribbling is common even after a successful urethral lengthening. At the outpatient clinic, you can be shown how to massage the urine out of the urethra.
- Loss of (sexual) sensation/orgasm: It is not possible to say with certainty whether sensation will return to the entire penis. Both the nerves from the skin and those from the former clitoris need to regrow after the operation. This process takes months and is difficult to predict. The main factors influencing this are your age and smoking habits. Because the clitoris is buried, it is often more difficult to experience an orgasm. Sometimes it becomes impossible. However, this complication is rare. Sensation in the penis after a phalloplasty is considerably less than sensation in the penis after a metoidioplasty.
Inflammation or post-operative bleeding may also occur at the site where the donor skin was removed (on the forearm, thigh or flank).
Final result
The final result varies from person to person. The appearance is partly determined by your current genitalia and the characteristics of the donor skin. It is impossible to predict in advance what the penis will look like. You cannot, therefore, make any requests regarding the appearance of the penis beforehand. You will have scars after the operation. The formation of scar tissue varies from person to person, depending on skin type and surgical technique. The specific technique used for you will depend on your skin and physique. The surgeon will determine which technique is best used for your phalloplasty. Everyone, and every type of skin, heals in their own way. In people who are overweight and those who smoke, scars tend to heal less aesthetically pleasing than in people of a healthy weight who do not smoke.
Secondary corrections
If, following the operation, you are still not entirely satisfied with the appearance or function of your genitals, please discuss this with your plastic surgeon or urologist. They will be able to advise you on whether further surgery could lead to improvements. Only once all secondary corrections have been completed can you have any desired prostheses fitted. An example of a secondary correction is a correction of the urethra, to improve the urine stream or to remedy leakage. A correction of the scrotum may also be desirable if the scars are very noticeable or if the scrotum is too small or asymmetrical. In principle, secondary corrections are not carried out within 6 months of the first operation. It is advisable to wait at least one year between operations to allow the genitals to heal as much as possible. Most secondary corrections are covered by health insurance; if in doubt, please contact your health insurer.
Examples of secondary corrective procedures
Urethral correction
If the urine stream is directed in the wrong direction or if the urethra is narrowed (stenosis), a correction may offer a solution. Leakage in the urethra may also occur, which needs to be repaired. Problems with the urethra may also arise following the insertion of a penile prosthesis, and corrective procedures may be necessary. Discuss the treatment options with the plastic surgeon and/or urologist. Usually, a urethral correction is covered by insurance.
Shape of the penis/creation of a glans
If you are unhappy with the shape of your penis, or if a glans has not yet been created, this can be carried out as a secondary corrective procedure. The glans can also be tattooed onto the tip of the penis; this is a minor procedure carried out under local anesthetic. Discuss the treatment options with your plastic surgeon. Contact your health insurer if you would like to know more about specific reimbursement arrangements.
Prosthetics
Following genital surgery for masculinisation, prostheses may be fitted. Testicular prostheses and penile prostheses are possible following a phalloplasty.
Sexual activity
Sexual activity is different for everyone and important to most people. Once your penis has healed sufficiently, sex is possible. Guidelines suggest that this is around three months after the operation; we advise you to discuss this during your follow-up appointments with
the plastic surgeon.
For more information about sexual activity after phalloplasty surgery, please visit this page.
This text was edited on 3-11-2026
Next Step
We recommend that you go through all the information chapters step by step to get a complete picture of the various treatment options and the process involved!We strive to keep this information up to date. Do you have any additions or comments regarding the information above? Please email us at [email protected]

Back to overview
Prostheses after genital surgery
On this page, you can read more about the various prosthesis options available following genital surgery and the different functions of these prostheses.

